The Mediating Role of Self-Esteem in the Relationship of Social Support and Resilience with Anxiety and Depression among Female Heads of Households
Keywords:
Female heads of households, social support, resilience, self-esteem, depression, anxietyAbstract
The present study aimed to investigate the mediating role of self-esteem in the relationship of social support and resilience with anxiety and depression among female heads of households in Shiraz. This descriptive-correlational study used a cross-sectional design. The statistical population consisted of all female heads of households in Shiraz in 2025, from whom 240 participants were selected through convenience sampling. Data were collected using the Rosenberg Self-Esteem Scale, the Multidimensional Scale of Perceived Social Support, the Connor-Davidson Resilience Scale, the Beck Depression Inventory, and the Good Existential Anxiety Questionnaire, and were analyzed using structural equation modeling. The findings indicated that the conceptual model had an acceptable fit. Social support had a direct negative effect on depression and a direct positive effect on self-esteem. Resilience also had a direct positive effect on self-esteem; however, its direct effect on anxiety was not significant. Self-esteem had direct negative effects on both depression and anxiety. Bootstrap analysis showed that self-esteem significantly mediated the relationships between social support and depression and anxiety, as well as the relationships between resilience and depression and anxiety. The findings suggest that self-esteem, as an important psychological mechanism, helps explain the relationships of external resources, such as social support, and internal resources, such as resilience, with the mental health of female heads of households. In addition, the non-significant direct effect of resilience on anxiety suggests that the association between resilience and anxiety may be explained through cognitive and self-worth mechanisms, including self-esteem.
Show full article content
Introduction
The family constitutes one of the most fundamental social institutions through which economic provision, emotional security, socialization, caregiving, and the organization of everyday life are maintained. Although households have traditionally been conceptualized as relatively stable social and economic units, changes in marital patterns, mortality, migration, economic insecurity, separation, and divorce have contributed to a growing diversity of household structures and have increased the visibility of households in which women assume primary responsibility for economic and familial management (1). Female-headed households represent a particularly important social group because the position of household head often requires women to undertake multiple and simultaneous responsibilities related to income generation, parenting, domestic management, decision-making, and the emotional needs of family members. In Iran, female-headed households have increasingly been discussed in relation to vulnerability, social welfare, and empowerment, with evidence indicating that vulnerability in this population is heterogeneous and reflects the interaction of economic, social, familial, and personal conditions rather than a single source of disadvantage (2). Psychological functioning is therefore an essential dimension of understanding the well-being of these women. Recent evidence concerning Iranian female-headed households has drawn particular attention to mental health and the factors associated with psychological well-being in this population (3). At the same time, intervention research among female heads of households has shown that psychological resources such as adjustment and psychological capital can be strengthened through structured psychological approaches, suggesting that the adverse consequences associated with difficult life circumstances are not fixed or inevitable (4). Accordingly, examining the psychological mechanisms that may protect women who carry the primary responsibility for their households is important not only for theoretical explanations of vulnerability and adaptation but also for designing interventions that move beyond economic assistance toward the promotion of sustainable psychological functioning.
Anxiety and depression are among the most prominent forms of psychological distress and can affect cognitive functioning, motivation, interpersonal relationships, occupational performance, physical health, and overall quality of life. Depression commonly involves persistent sadness, loss of interest or pleasure, reduced motivation, negative self-evaluation, hopelessness, and impaired functioning, whereas anxiety is characterized by heightened apprehension, excessive worry, anticipatory threat, physiological arousal, and difficulty maintaining a sense of psychological security. Contemporary research emphasizes that both conditions are multidetermined and emerge through interactions among biological, psychological, behavioral, and social processes rather than through a single causal pathway. For example, evidence concerning the gut–brain axis has highlighted the complex biological mechanisms potentially involved in anxiety and depression and has reinforced the view that these disorders should be understood within a multidimensional biopsychosocial framework (5). Similarly, research among clinical populations demonstrates that anxiety and depression frequently coexist with chronic physical illness and can substantially complicate adaptation and functioning, illustrating the broad relevance of these conditions across health contexts (6). Studies conducted in Iranian populations have also documented the importance of demographic and psychosocial correlates of anxiety and depression, including evidence among adolescent girls indicating that these symptoms represent meaningful public-health concerns across different groups of women (7). Furthermore, the relationship between behavioral and demographic characteristics and symptoms of anxiety and depression, including differences associated with age and gender, suggests that psychological distress should be investigated in relation to the specific circumstances of the target population rather than assumed to operate identically across groups (8). For female heads of households, this contextual perspective is particularly important because ongoing economic demands, responsibility for dependents, possible social isolation, uncertainty regarding the future, and the need to perform multiple family roles may generate chronic rather than episodic stress. Such conditions can increase the salience of internal and interpersonal resources that shape how stress is appraised, managed, and translated into symptoms of anxiety and depression.
Among the most important external resources associated with psychological adaptation is social support. Social support broadly refers to the emotional, informational, instrumental, and relational resources that individuals perceive as available from family members, friends, significant others, and wider social networks. Perceived support may provide reassurance during adversity, reduce feelings of isolation, facilitate access to practical help, increase confidence in coping resources, and communicate that the individual is accepted and valued. Research has consistently linked stronger supportive relationships with more favorable psychological and social outcomes across populations. In Iranian research, perceived social support has been associated with depression through psychologically meaningful pathways, demonstrating that the availability and perception of supportive resources may influence emotional well-being even in populations exposed to age-related vulnerabilities (9). Social support has also been linked with family health and social adjustment, indicating that its effects extend beyond individual emotional states to broader patterns of social and familial functioning (10). A meta-analytic study further demonstrated a positive relationship between social support and academic performance, illustrating that supportive relationships may contribute not only to mental health but also to effective functioning and achievement in demanding environments (11). Evidence from perinatal populations similarly indicates that social support is meaningfully related to both depression and anxiety, with mixed-method findings emphasizing the importance of how support is experienced and perceived rather than merely whether social contacts are objectively present (12). These findings are particularly relevant to female heads of households because responsibility for both economic provision and family care may increase the practical and emotional value of dependable support. When women perceive that assistance, understanding, validation, and companionship are available, stressful circumstances may be experienced as more manageable; conversely, insufficient or unreliable support may intensify loneliness, overload, and perceived helplessness. Thus, social support may function as a direct protective factor against psychological distress while also influencing more proximal psychological characteristics through which emotional outcomes are shaped.
Resilience constitutes an important internal resource that may complement the protective role of social support. Psychological resilience generally refers to the capacity to maintain, recover, or re-establish adaptive functioning when confronted with adversity, uncertainty, prolonged stress, or significant life challenges. Rather than implying the absence of distress, resilience reflects flexible adaptation, persistence, effective use of coping resources, and the ability to sustain or reconstruct psychological equilibrium under difficult conditions. The importance of resilience has been demonstrated in research examining depression and anxiety during periods of widespread adversity; a systematic review of the general adult population during the COVID-19 pandemic found that individual resilience was meaningfully associated with lower levels of depression and anxiety, supporting its role as a protective psychological capacity (13). Resilience is also strengthened by interpersonal and contextual resources. Evidence among young people indicates that social support can contribute to resilience and that coping styles help explain part of this relationship, suggesting that external and internal protective resources should not be regarded as independent domains (14). The concept of resilience has, moreover, been employed beyond individual psychology to describe the capacity of systems to withstand disturbances and preserve functioning. Post-COVID-19 research on supply-chain resilience, for example, has emphasized adaptation, recovery, flexibility, and continuity following disruption (15); likewise, ecological research demonstrating that habitat size can influence community stability illustrates the broader scientific principle that stability depends partly on the resources and structural conditions available to a system (16). Although these systemic findings operate at different levels of analysis and should not be equated directly with psychological resilience, they underscore a common conceptual emphasis on maintaining or restoring functioning under adverse conditions. For female heads of households, resilience may therefore represent the capacity to respond adaptively to persistent financial, familial, and social demands, maintain a future-oriented perspective, and preserve psychological functioning despite repeated stressors. However, resilience may not influence anxiety and depression exclusively through direct coping processes; its protective consequences may also depend on how successful adaptation affects women's perceptions of their own worth and competence.
Self-esteem is particularly relevant in this regard because it concerns the individual's general evaluation of personal worth, adequacy, and value. Self-esteem influences how people interpret social feedback, evaluate their abilities, respond to failure, and assess their capacity to manage difficult circumstances. Contemporary evidence indicates that high self-esteem is not merely a pleasant subjective state but is associated with numerous favorable indicators of psychological and social functioning, although its consequences should be understood carefully and in relation to broader personality and contextual factors (17). Conversely, diminished self-esteem can intensify vulnerability to self-criticism, feelings of incompetence, rejection sensitivity, helplessness, and negative emotional states. Experimental evidence concerning social exclusion has shown that exclusion can affect explicit and implicit dimensions of self-esteem and that dispositional self-esteem may influence responses to exclusion, highlighting the close connection between interpersonal experiences and self-evaluation (18). Self-esteem is also associated with subjective satisfaction in educational contexts, further demonstrating its relationship with broader evaluations of personal and life functioning (19). At the same time, modern social environments expose individuals to powerful evaluative pressures. Research on social media indicates that digitally mediated comparison and feedback can influence self-esteem, illustrating the susceptibility of self-evaluation to interpersonal and sociocultural experiences (20). Reviews of body perception, social media, psychological well-being, and mental health similarly indicate that self-esteem is closely intertwined with body satisfaction, cultural norms, and gender-related influences (21). These considerations may be especially important for female heads of households, whose self-perceptions can develop in contexts shaped by gender expectations, financial independence, family responsibility, social judgment, and the perceived adequacy with which multiple roles are fulfilled. When persistent pressures are interpreted as evidence of personal inadequacy, self-esteem may decline and emotional distress may increase; when challenges are met with a sustained sense of competence and personal worth, the psychological consequences of adversity may be attenuated.
The relationship between self-esteem and emotional distress is supported by evidence indicating that self-evaluation can predict anxiety-related outcomes over time. Longitudinal research among university students has shown that self-esteem functions as a predictor of anxiety as well as academic self-efficacy, reinforcing the possibility that self-esteem precedes and contributes to subsequent emotional and competence-related outcomes rather than merely reflecting concurrent well-being (22). Research examining family functioning and clinical symptoms of anxiety has likewise identified self-esteem as an important mediator, suggesting that characteristics of the interpersonal environment may affect anxiety partly through their consequences for how individuals evaluate themselves (23). Such findings are theoretically compatible with a mediation framework in which supportive and adaptive resources strengthen self-worth and, through enhanced self-worth, reduce vulnerability to depression and anxiety. Social support may contribute to self-esteem because supportive interactions convey acceptance, belonging, recognition, and interpersonal value. When individuals repeatedly experience themselves as worthy of care and assistance, these social appraisals may gradually be internalized into more favorable self-evaluations. Resilience may similarly enhance self-esteem because coping successfully with adversity can provide repeated experiential evidence of competence, persistence, and personal effectiveness. Consequently, self-esteem may be positioned at the intersection between external social resources and internal adaptive capacities. It can transform the meaning of support and resilience into a more stable sense of personal worth, which may then reduce maladaptive cognitions associated with anxiety and depression. This proposition is especially plausible among female heads of households because their social circumstances can make both recognition from others and confidence in personal competence particularly consequential for psychological well-being.
The proposed mediating role of self-esteem is also supported by evidence directly linking social support with affective functioning through self-evaluative processes. Among undergraduate students, self-esteem has been shown to mediate the relationship between social support and affective experiences, indicating that supportive interpersonal environments may influence emotional states partly because they strengthen positive self-regard (24). Although university students differ substantially from female heads of households in developmental stage, responsibilities, socioeconomic conditions, and sources of stress, the underlying psychological mechanism may be transferable: social support can communicate interpersonal acceptance, while self-esteem represents the internalized appraisal through which such acceptance affects emotional experience. Family relationships may be particularly relevant because family processes are strongly associated with psychosocial outcomes throughout development. A systematic review and meta-analysis concerning parenting and bullying among children and adolescents demonstrates the broader importance of family and parenting contexts for vulnerability and adjustment, underscoring the long-term significance of relational environments for psychological functioning (25). For women responsible for heading households, family relationships may operate in both directions: they are providers of support and caregiving to dependents while simultaneously requiring support, recognition, and cooperation from relatives and other significant people. This dual role may make the subjective quality of social support especially important. At the same time, female heads of households who possess greater resilience may be more likely to interpret demanding circumstances as challenges that can be managed rather than as evidence of inevitable failure, thereby preserving self-respect under adversity. Self-esteem may therefore provide a parsimonious explanatory mechanism connecting two distinct classes of protective resources—social support as an interpersonal resource and resilience as an intrapersonal adaptive resource—with two closely related indicators of psychological distress, namely anxiety and depression.
Despite increasing research on social support, resilience, self-esteem, anxiety, and depression, important gaps remain. Much of the available evidence examines these constructs separately or in populations such as adolescents, students, older adults, clinical groups, or women during specific reproductive periods, and therefore may not adequately represent women who continuously carry primary economic and family responsibility. Moreover, research demonstrating that self-esteem mediates the effects of family functioning or social support has frequently focused on younger populations rather than socially and economically vulnerable adult women (23, 24). Similarly, although resilience is consistently associated with lower anxiety and depression in general adult populations (13), comparatively less attention has been given to whether its effects operate through self-esteem among female heads of households. This distinction is theoretically important because demonstrating only direct associations does not clarify the psychological processes through which external and internal resources become translated into mental-health outcomes. It is also practically important because mediation models identify potentially modifiable targets for intervention. If social support and resilience are related to lower anxiety and depression partly because they strengthen self-esteem, interventions could be designed not only to expand support networks and coping abilities but also to help women recognize competence, challenge negative self-evaluations, and develop a more stable sense of personal worth. Such an integrated approach is consistent with emerging evidence that mental health among female-headed households reflects multiple intersecting sources of vulnerability and protection rather than isolated risk factors (2, 3). Accordingly, the present study aimed to investigate the mediating role of self-esteem in the relationships of social support and resilience with anxiety and depression among female heads of households.
Methods and Materials
Study Design and Participants
This study was cross-sectional in terms of time and descriptive-correlational in design. Its aim was to examine the mediating role of self-esteem in the relationship of social support and resilience with anxiety and depression among female heads of households. The statistical population consisted of all female heads of households in Shiraz in 2025. A convenience sample of 240 women was selected. Of the 240 questionnaires, 10 were excluded because of incomplete responses or outlying data, leaving 230 cases for analysis. Because structural equation modeling and path analysis were used to test relationships among the variables, sample size was determined on the basis of recommendations from authoritative sources in structural equation modeling. According to Tabachnick and Fidell (2019), the minimum sample size required for regression- and path-analysis models can be estimated using N >= 50 + 8m for testing the overall model and N >= 104 + m for testing individual predictor coefficients, where m represents the number of predictor variables; for the present model, this yielded an estimate of approximately 110 participants. However, many structural equation modeling authorities regard such values as minimum requirements and recommend larger samples to obtain more stable estimates. In this regard, Kline (2023) recommends a sample size of approximately 200 to achieve adequate model fit and reliable estimates. After collection, questionnaire data were analyzed using SPSS version 27 at descriptive and inferential levels. Descriptive indices included the mean, standard deviation, minimum, and maximum values of the study variables. At the inferential level, Pearson correlation coefficients, regression, and structural equation modeling were used to test the study hypotheses. All ethical principles applicable to research with human participants were observed. Before the study began, the required approval was obtained from the university research ethics committee, after which the aims and procedures were fully explained to all participants. Written informed consent was obtained from every participant, and they were assured that they could withdraw from the study at any stage without any consequences. Participants were also informed that their information would remain confidential and would be analyzed only in coded form without identifying names. The ethics approval code was IR.IAU.A.REC.1404.071.
Data Collection Tools
Rosenberg Self-Esteem Scale (1965): The Rosenberg Self-Esteem Scale was developed by Morris Rosenberg in 1965 at the University of Maryland, United States. It is one of the most widely used and well-established measures of self-esteem in social, clinical, and educational psychology. Its primary purpose is to assess an individual's overall attitude toward the self and personal sense of worth. It is a self-report instrument suitable for different age groups. The scale consists of 10 items rated on a four-point Likert scale ranging from strongly agree to strongly disagree. International studies have supported its construct and convergent validity. Rosenberg reported that the measure correlates strongly with other measures of self-esteem, depression, anxiety, and mental health. Across international studies, Cronbach's alpha coefficients have ranged from 0.77 to 0.88, and two-week test-retest reliability has been approximately 0.85. In Iranian studies, content validity has been confirmed by psychologists, and confirmatory factor analysis has supported a one-factor structure. In domestic studies, Cronbach's alpha coefficients have ranged from 0.78 to 0.84, indicating satisfactory reliability in Iranian populations.
Multidimensional Scale of Perceived Social Support (Zimet et al., 1988): The Multidimensional Scale of Perceived Social Support (MSPSS) was developed by Zimet, Dahlem, Zimet, and Farley in 1988 to assess perceived social support from three principal sources: family, friends, and a significant other. It is among the most widely used and validated measures in psychological, social, and mental health research and can be used across different age groups. The questionnaire contains 12 items divided into three subscales - family support, friend support, and significant-other support - with four items in each subscale. Responses are scored on a seven-point Likert scale from 1 (strongly disagree) to 7 (strongly agree). Item scores range from 1 to 7, subscale scores from 4 to 28, and the total score from 12 to 84. International studies have supported the construct, convergent, and discriminant validity of the MSPSS, and the measure shows significant relationships with depression, anxiety, life satisfaction, and self-esteem. Cronbach's alpha coefficients have ranged from 0.85 to 0.92 for the total scale and from 0.81 to 0.90 for the subscales. Iranian studies have confirmed the three-factor structure by factor analysis and have supported its content validity. Domestic studies have reported Cronbach's alpha coefficients ranging from 0.84 to 0.90 for the total scale, indicating satisfactory reliability in Iranian populations.
Connor-Davidson Resilience Scale (2003): The Connor-Davidson Resilience Scale (CD-RISC) was developed by Kathryn Connor and Jonathan Davidson in 2003 to assess individuals' resilience in the face of stress, psychological pressure, and difficult life circumstances. The original CD-RISC contains 25 items, and shorter 10-item and 2-item versions were subsequently developed. The scale has been widely used in psychiatry, clinical psychology, mental health research, and social studies. In the original 25-item version, responses are rated on a five-point Likert scale from 0 (not true at all) to 4 (true nearly all of the time). International research has supported its construct, convergent, and discriminant validity, and the measure is significantly associated with depression, anxiety, self-esteem, and mental health. Cronbach's alpha coefficients for the 25-item version have ranged from 0.89 to 0.92, with one-month test-retest reliability of approximately 0.87. In Iranian studies, both one-factor and multifactor structures have been supported through factor analysis, and content validity has been confirmed by psychologists. Domestic studies have reported Cronbach's alpha coefficients ranging from 0.85 to 0.90 for the 25-item version, indicating satisfactory reliability in Iranian populations.
Beck Depression Inventory (1961): The Beck Depression Inventory-II (BDI-II) was developed and published by Aaron T. Beck, Robert A. Steer, and Gregory Brown in 1996 as a revision of the original Beck Depression Inventory (1961) and was aligned with DSM-IV diagnostic criteria. Its primary purpose is to assess the severity of depressive symptoms in adults and adolescents aged 13 years and older. The BDI-II is one of the best-established screening and assessment instruments for depression in clinical psychology, psychiatry, and mental health research. It consists of 21 items, each describing a depressive symptom or state. Respondents select one of four options (0-3) indicating the severity of that symptom during the previous two weeks. International research has supported its construct, convergent, and diagnostic validity, and the instrument correlates strongly with other measures of depression. Cronbach's alpha coefficients across studies have ranged from 0.85 to 0.92, and one- to two-week test-retest reliability has been approximately 0.83. In Iranian studies, content validity has been supported by psychology experts and factor structure has been confirmed using factor analysis. Domestic studies have reported Cronbach's alpha coefficients ranging from 0.87 to 0.90, indicating satisfactory reliability in Iranian populations.
Good Existential Anxiety Questionnaire (1974): The Good Existential Anxiety Questionnaire was developed by Lawrence and Catherine Good in 1974. Its primary purpose is to assess existential anxiety arising from awareness of death, freedom, loneliness, and the meaninglessness of life. The questionnaire is used in clinical psychology, counseling, and mental health research and was designed specifically to examine philosophical and existential dimensions of anxiety. It contains 32 items rated on a five-point Likert scale ranging from strongly disagree to strongly agree. Each item is scored from 1 to 5, yielding a total score from 32 to 160. International studies have supported the construct and convergent validity of this questionnaire. Halt (1994) reported significant correlations with measures of purpose in life and depression. Cronbach's alpha has been reported at approximately 0.88 in international studies, and split-half coefficients have exceeded 0.87. In Iranian studies, content validity has been supported by psychology experts and factor analysis has indicated an acceptable structure. Cronbach's alpha coefficients of approximately 0.85 to 0.88 have been reported in Iranian samples, indicating satisfactory reliability.
Data Analysis
Raw quantitative data were collected in the field using the study questionnaires and were analyzed with SPSS and AMOS using appropriate descriptive and inferential statistical techniques. Descriptive analyses included the mean and standard deviation of scores, while inferential analyses used Pearson correlation, regression, and structural equation modeling to test the study hypotheses.
Findings and Results
Table 1 presents the descriptive statistics for the study variables, including the mean, standard deviation, minimum, maximum, and sample size.
Variable | Mean | SD | Minimum | Maximum | N |
|---|---|---|---|---|---|
Depression | 21.57 | 8.30 | 11 | 62 | 230 |
Anxiety | 90.80 | 13.81 | 72 | 156 | 230 |
Self-esteem | 20.99 | 3.70 | 14 | 28 | 230 |
Social support | 56.70 | 7.67 | 33 | 79 | 230 |
Resilience | 70.96 | 6.07 | 50 | 80 | 230 |
As shown in Table 2, Pearson correlation coefficients indicated that resilience was negatively and significantly associated with depression (r = -0.48, p < .01) and anxiety (r = -0.44, p < .01), but positively and significantly associated with self-esteem (r = 0.47, p < .01) and social support (r = 0.44, p < .01). Social support was negatively and significantly associated with depression (r = -0.71, p < .01) and anxiety (r = -0.66, p < .01), but positively and significantly associated with self-esteem (r = 0.78, p < .01). Finally, self-esteem was negatively and significantly associated with depression (r = -0.65, p < .01) and anxiety (r = -0.70, p < .01).
Variable | 1 | 2 | 3 | 4 | 5 |
|---|---|---|---|---|---|
1. Depression | 1 | ||||
2. Anxiety | 0.63** | 1 | |||
3. Self-esteem | -0.65** | -0.70** | 1 | ||
4. Social support | -0.71** | -0.66** | 0.78** | 1 | |
5. Resilience | -0.48** | -0.44** | 0.47** | 0.44** | 1 |
As shown in Table 3, after non-significant paths were removed, the proposed model demonstrated an adequate fit (χ²/df = 2.37, RMSEA = 0.07), and the model was therefore accepted. The high values of the goodness-of-fit indices indicate good model fit. In addition, an RMSEA value of 0.07 indicates an acceptable approximation error and adequate model fit (Karshki, 1391, pp. 50-53).
Fit index | χ²/df | GFI | AGFI | TLI | CFI | NFI | IFI | RMSEA |
|---|---|---|---|---|---|---|---|---|
Acceptable value | 1-3 | ≥ 0.90 | ≥ 0.90 | ≥ 0.90 | ≥ 0.90 | ≥ 0.90 | ≥ 0.90 | ≤ 0.10 |
Final model | 2.37 | 0.96 | 0.92 | 0.94 | 0.95 | 0.96 | 0.94 | 0.07 |
The fit indices of the final model indicated that the proposed model fit the data adequately. The chi-square-to-degrees-of-freedom ratio (2.37) was within the acceptable range of 1 to 3. The absolute fit indices GFI = 0.96 and AGFI = 0.92 both exceeded the criterion value of 0.90 and supported good model fit. Likewise, the comparative fit indices TLI = 0.94, CFI = 0.95, NFI = 0.96, and IFI = 0.94 all exceeded 0.90, indicating very good fit. RMSEA was 0.07, which was below the criterion value of 0.10 and indicated low approximation error and acceptable fit to the study data. Overall, the obtained fit indices show that the final model had acceptable fit and was appropriate for testing the research hypotheses.

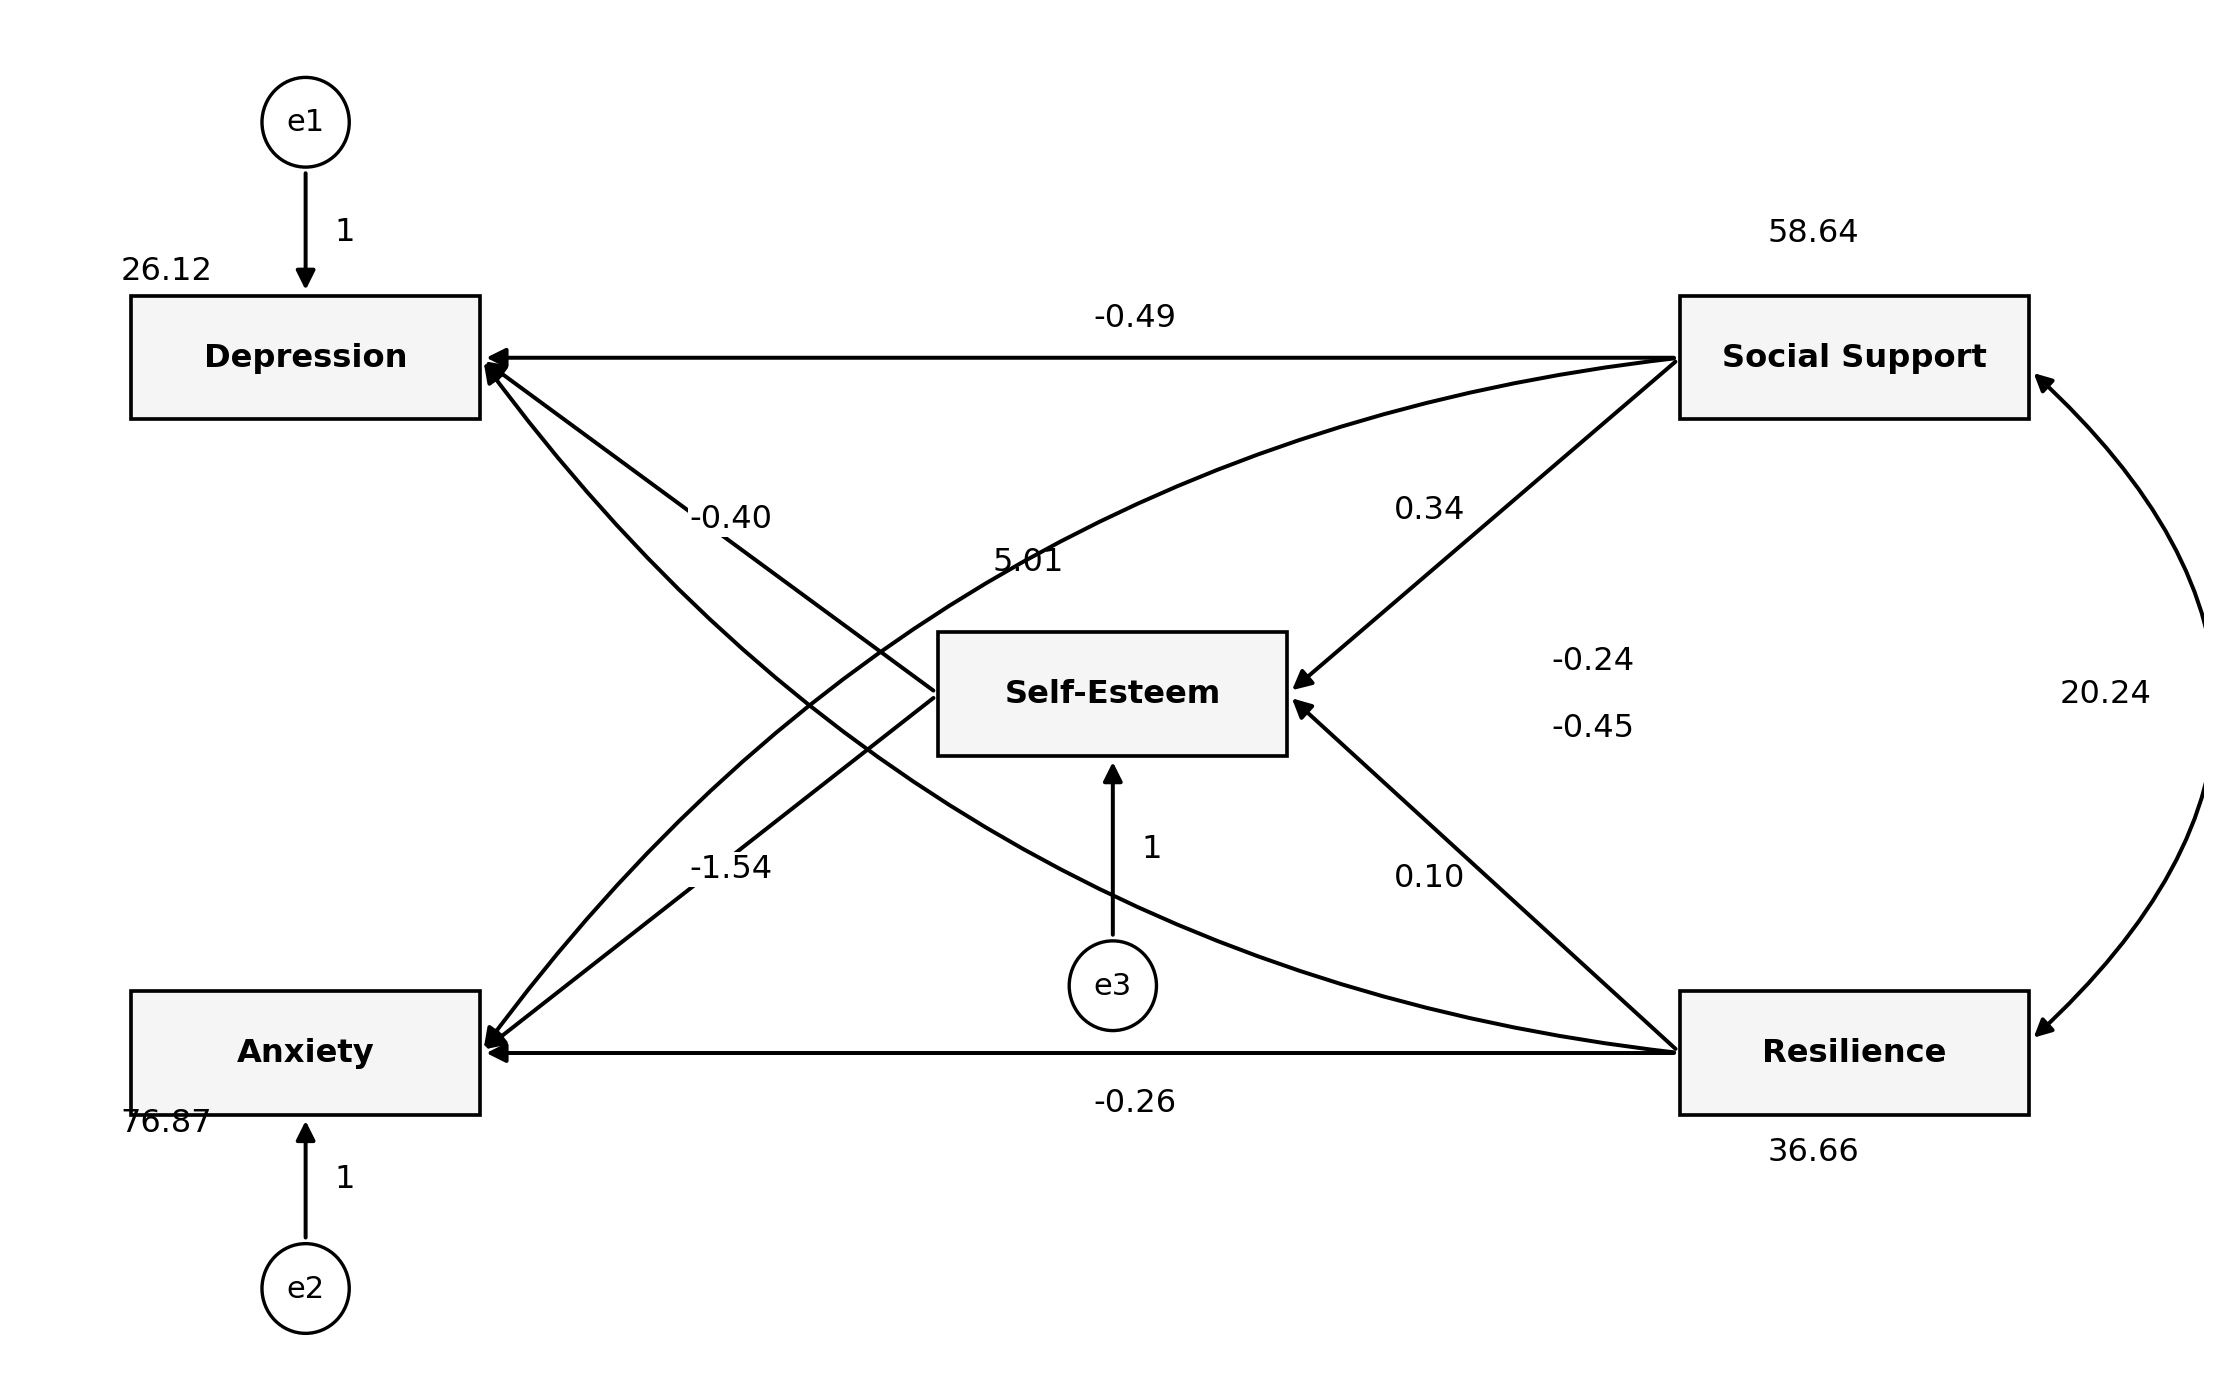
Table 4 presents the standardized and unstandardized coefficients, standard errors, critical ratios (calculated by dividing the unstandardized coefficient B by its standard error), and significance levels. The beta coefficient (the standardized weight for each path) reflects the role of a variable in estimating or predicting the subsequent variable along that path. The critical ratio indicates how far a parameter estimate differs from zero, with larger absolute values indicating greater differences. The significance level indicates whether a path variable has a statistically significant effect in predicting the subsequent variable.
Path | Standardized estimate (β) | Unstandardized estimate (B) | SE | Critical ratio | p |
|---|---|---|---|---|---|
Social support → Self-esteem | 0.71 | 0.34 | 0.02 | 15.99 | 0.001 |
Resilience → Self-esteem | 0.16 | 0.10 | 0.027 | 3.60 | 0.001 |
Self-esteem → Depression | -0.19 | -0.40 | 0.15 | -2.62 | 0.009 |
Self-esteem → Anxiety | -0.44 | -1.54 | 0.26 | -5.96 | 0.001 |
Social support → Depression | -0.49 | -0.49 | 0.07 | -6.86 | 0.001 |
Social support → Anxiety | -0.27 | -0.45 | 0.12 | -3.67 | 0.001 |
Resilience → Anxiety | -0.12 | -0.26 | 0.11 | -2.35 | 0.019 |
Resilience → Depression | -0.19 | -0.24 | 0.06 | -3.72 | 0.001 |
The standardized beta coefficients in Table 4 indicate that social support had a positive and significant effect on self-esteem (β = 0.71, p < .001), and resilience also had a positive and significant effect on self-esteem (β = 0.16, p < .001). In contrast, self-esteem had significant negative effects on depression (β = -0.19, p = .009) and anxiety (β = -0.44, p < .001); social support had significant negative effects on depression (β = -0.49, p < .001) and anxiety (β = -0.27, p < .001); and resilience had significant negative effects on anxiety (β = -0.12, p < .05) and depression (β = -0.19, p < .001).
To examine the significance of indirect (mediated) effects, bootstrap analysis was used. This method is one of the most powerful approaches for testing indirect effects because it repeatedly resamples the observed data to estimate the sampling distribution of an indirect effect without requiring an assumption of normality for that distribution (Preacher & Hayes, 2008). In the present study, bootstrap analysis was conducted with 2,000 resamples and a 95% confidence level. Statistical significance was determined by examining the 95% confidence interval: if zero did not fall within the interval (i.e., both the lower and upper limits were positive or both were negative), the indirect effect was considered significant at the 0.05 level. The bootstrap results are presented in Table 5. As shown, none of the 95% confidence intervals for the indirect effects included zero, indicating significant indirect effects in the research model.
Predictor | Mediator | Outcome | Indirect effect | Lower limit | Upper limit | p |
|---|---|---|---|---|---|---|
Social support | Self-esteem | Anxiety | -0.314 | -0.532 | -0.145 | 0.001 |
Social support | Self-esteem | Depression | -0.135 | -0.277 | -0.037 | 0.006 |
Resilience | Self-esteem | Anxiety | -0.071 | -0.154 | -0.022 | 0.001 |
Resilience | Self-esteem | Depression | -0.030 | -0.081 | -0.006 | 0.005 |
As shown in Table 5, self-esteem had a significant mediating role in the relationship between social support and anxiety (β = -0.314, p < .001) and between social support and depression (β = -0.135, p = .006). Self-esteem also significantly mediated the relationship between resilience and anxiety (β = -0.071, p < .001) and between resilience and depression (β = -0.030, p = .005). The model explained 63% of the variance in self-esteem (R² = 0.63), 56% of the variance in depression (R² = 0.56), and 54% of the variance in anxiety (R² = 0.54).
Discussion and Conclusion
The present study examined the mediating role of self-esteem in the relationships of social support and resilience with anxiety and depression among female heads of households. The structural model demonstrated an acceptable fit with the observed data, with χ²/df = 2.37, GFI = 0.96, AGFI = 0.92, TLI = 0.94, CFI = 0.95, NFI = 0.96, IFI = 0.94, and RMSEA = 0.07. The model explained 63% of the variance in self-esteem, 56% of the variance in depression, and 54% of the variance in anxiety. Social support had a strong positive direct effect on self-esteem (β = 0.71, p < .001) and significant negative direct effects on depression (β = −0.49, p < .001) and anxiety (β = −0.27, p < .001). Resilience also positively predicted self-esteem (β = 0.16, p < .001) and negatively predicted both depression (β = −0.19, p < .001) and anxiety (β = −0.12, p = .019). Self-esteem, in turn, negatively predicted depression (β = −0.19, p = .009) and anxiety (β = −0.44, p < .001). Bootstrap analysis further indicated significant indirect effects of social support on anxiety (β = −0.314, p = .001) and depression (β = −0.135, p = .006) through self-esteem, as well as significant indirect effects of resilience on anxiety (β = −0.071, p = .001) and depression (β = −0.030, p = .005) through self-esteem. These findings collectively indicate that the mental health of female heads of households is shaped by a network of external and internal resources and that self-esteem constitutes an important psychological mechanism through which these resources are associated with reduced emotional distress.
The significant negative relationship between social support and depression indicates that women who perceive greater emotional, informational, instrumental, and relational support are less likely to experience depressive symptoms. This finding is consistent with evidence demonstrating that perceived social support is closely associated with depression and other indicators of psychological functioning. Hashemi et al. reported that perceived social support was significantly related to depression, emphasizing that supportive social relationships can contribute to better psychological outcomes even in populations exposed to multiple vulnerabilities (9). Similarly, the systematic review by Sufredini et al. showed that social support plays an important protective role against depression and anxiety, with emotional and practical support helping individuals cope with stressful circumstances (12). The present finding can be explained by the stress-buffering function of social support. Female heads of households often face simultaneous economic, caregiving, occupational, and social responsibilities, and these demands may become psychologically burdensome when they are experienced in isolation. Support from relatives, friends, significant others, and social institutions may reduce this burden by providing practical assistance, emotional validation, and reassurance that difficult circumstances do not have to be managed alone. Social support may also strengthen family functioning and social adjustment, as suggested by evidence linking supportive resources with family health (10). Thus, when female heads of households perceive that reliable support is available, stressful events may be appraised as more manageable and less overwhelming, reducing feelings of helplessness, social disconnection, and hopelessness that are commonly associated with depressive states.
Social support also had a significant negative direct effect on anxiety. This result is compatible with previous findings demonstrating that greater social support is associated with lower anxiety across different populations (12). Anxiety frequently involves uncertainty, anticipatory threat, excessive worry, and concerns regarding one's ability to cope with future demands. For female heads of households, such concerns may center on income stability, children's needs, family management, health, social security, and unexpected life events. Under such conditions, supportive relationships can create a subjective sense of safety and predictability because the individual knows that emotional or practical assistance is available if difficulties occur. This interpretation is also compatible with findings suggesting that supportive social environments contribute to broader psychological and behavioral functioning (11). Social support may therefore reduce anxiety not only by solving practical problems but also by altering cognitive appraisals of threat. When women perceive themselves as embedded in reliable social networks, they may evaluate future challenges as less uncontrollable and may feel more confident about their ability to cope. In this sense, social support functions simultaneously as an interpersonal resource and as a source of psychological security, which is particularly important in a population characterized by heightened economic and familial responsibility.
Another important finding was the positive effect of social support on self-esteem. This result is strongly consistent with the study of Yıldırım et al., which demonstrated that self-esteem plays a mediating role in the relationship between social support and affective experiences among undergraduate students (24). Although the populations differ, the underlying psychological process is likely similar. Social support communicates acceptance, belonging, interpersonal worth, and recognition. Repeated experiences of being valued and supported by significant others can become incorporated into an individual's self-concept, thereby strengthening self-esteem. This interpretation is particularly relevant for female heads of households because social expectations, economic difficulties, and the burden of performing multiple roles may expose them to experiences that undermine perceived competence or personal worth. Social exclusion has been shown to affect both explicit and implicit aspects of self-esteem, highlighting the sensitivity of self-evaluation to interpersonal experiences (18). Accordingly, supportive relationships may operate in the opposite direction by providing positive interpersonal feedback that protects or restores self-worth. The strength of the observed path from social support to self-esteem in the present study suggests that interpersonal resources may be especially important for how female heads of households evaluate themselves.
The findings also indicated that resilience had significant negative effects on both depression and anxiety. This is consistent with the systematic review by Yap et al., which found that greater individual resilience was associated with lower depression and anxiety among adults exposed to the stress of the COVID-19 pandemic (13). Resilience enables individuals to maintain or restore adaptive functioning when they encounter adversity, uncertainty, and prolonged stress. Female heads of households frequently experience chronic rather than temporary stressors, including sustained responsibility for economic provision and family functioning. In this context, resilience may reduce depression by limiting hopelessness and promoting persistence, problem solving, and recovery following setbacks. It may reduce anxiety by increasing perceived control and decreasing the tendency to interpret stressors as overwhelming or unmanageable. The association between social support and resilience reported in previous research also suggests that resilience does not develop or operate exclusively as an isolated personal trait. Cao et al. showed that social support was associated with youth resilience and that coping styles contributed to this relationship (14). Therefore, resilience among female heads of households may reflect both personal adaptive capacities and successful utilization of environmental resources. Women who are able to respond flexibly to difficulties, mobilize available resources, and maintain psychological balance may consequently be less vulnerable to sustained anxiety and depressive symptoms.
Resilience also positively predicted self-esteem. One explanation is that successful adaptation to adversity provides repeated evidence of personal competence. Each time an individual manages a difficult situation, resolves a problem, or recovers from a stressful event, she gains experiential information indicating that she is capable of coping effectively. Over time, such experiences may contribute to a stronger global evaluation of personal worth and competence. This interpretation is compatible with the broader literature on self-esteem, which describes it as a consequential psychological resource associated with effective functioning and adjustment (17). For female heads of households, resilience may be particularly important in preserving self-esteem because successful management of family and economic challenges may counteract experiences of social devaluation, role overload, or perceived inadequacy. Although resilience is commonly treated as a protective factor in its own right, the present results indicate that part of its psychological benefit may arise because resilient adaptation strengthens positive self-appraisal. In this respect, resilience may influence mental health not only through direct coping mechanisms but also through the development of more favorable beliefs about the self.
A central finding of the study was that higher self-esteem predicted lower levels of both depression and anxiety, with the relationship being particularly strong for anxiety. This result is consistent with extensive evidence indicating that self-esteem is associated with emotional well-being and psychological adjustment (17). Cao and Liu also found that self-esteem predicted anxiety longitudinally, providing evidence that self-evaluation may precede and influence subsequent anxiety-related outcomes rather than simply being a consequence of emotional distress (22). Low self-esteem can increase depression through negative self-evaluation, feelings of inadequacy, diminished hope, and self-critical thinking, whereas high self-esteem may protect against these processes by maintaining a stable sense of worth during difficult circumstances. With respect to anxiety, self-esteem may affect how individuals evaluate their ability to manage potential threats. A woman who perceives herself as competent and worthy may interpret difficult events as challenging but manageable, whereas low self-esteem can magnify perceived vulnerability and uncertainty. The relationship between self-esteem and psychological functioning is also influenced by broader sociocultural and interpersonal contexts. Contemporary research has demonstrated that social comparison, cultural expectations, gender-related standards, and body perceptions can affect self-esteem and mental health (21), while social-media environments can contribute to fluctuations in self-evaluation (20). These findings further illustrate why self-esteem may be especially salient among women whose identities are simultaneously shaped by caregiving, financial responsibility, social evaluation, and gendered expectations.
The mediation findings provide the most important contribution of the present study. Self-esteem significantly mediated the relationships of social support with both depression and anxiety. These results are closely aligned with the findings of Yıldırım et al., who demonstrated that self-esteem acts as a mediator between social support and affective experiences (24). They are also consistent with research showing that self-esteem can mediate the relationship between family functioning and anxiety symptoms (23). The present findings indicate that social support may protect mental health through two complementary pathways. First, support has a direct protective effect by reducing isolation, providing resources, and facilitating coping. Second, social support strengthens self-esteem by communicating that the individual is accepted, valued, and worthy of assistance, and this more positive self-evaluation subsequently reduces psychological distress. This indirect mechanism is theoretically important because it explains why two individuals receiving objectively similar levels of assistance may experience different psychological outcomes. Support that is perceived as affirming personal value may be particularly effective because it changes not only the external situation but also the individual's internal representation of herself. Among female heads of households, such affirmation may counteract experiences of stigma, dependency, social judgment, or perceived failure and thereby reduce susceptibility to anxiety and depression.
Self-esteem also significantly mediated the relationships of resilience with anxiety and depression. This finding extends previous evidence by suggesting that resilience exerts part of its protective effect through self-evaluative processes. Although Yap et al. demonstrated a consistent inverse relationship of resilience with depression and anxiety (13), the present model clarifies one potential mechanism underlying these relationships. Resilient women may repeatedly experience themselves as capable of managing adversity, and these mastery experiences can strengthen self-esteem. Higher self-esteem can then reduce the negative cognitions and perceived vulnerability associated with depression and anxiety. This explanation is consistent with evidence that self-esteem predicts anxiety (22) and with broader theoretical accounts emphasizing the beneficial consequences of positive self-regard (17). The mediation effect was smaller for resilience than for social support, which is also compatible with the observed model because social support showed a substantially stronger association with self-esteem. This pattern suggests that, among female heads of households, interpersonal validation and perceived availability of others may be particularly influential in shaping self-worth, whereas resilience contributes more modestly but still significantly. Importantly, these results do not imply that resilience is unimportant; rather, they demonstrate that its relationship with emotional health is partly embedded within a broader psychological process involving beliefs about personal competence and worth.
Taken together, the findings support an integrated understanding of mental health among female heads of households. Their psychological functioning cannot be adequately explained only by exposure to stress or economic disadvantage. Instead, the impact of difficult circumstances appears to depend partly on whether women have access to supportive interpersonal resources, whether they possess adaptive capacities for coping with adversity, and whether these resources contribute to a stable and positive sense of self-worth. This interpretation is consistent with evidence that female-headed households constitute a heterogeneous population with different patterns of vulnerability and empowerment (2) and with recent attention to the mental health needs of Iranian female-headed households (3). The findings are also compatible with intervention evidence indicating that psychological resources among female heads of households can be enhanced rather than regarded as fixed characteristics (4). Thus, the present study adds to the literature by integrating social support, resilience, self-esteem, anxiety, and depression in a single structural model and demonstrating that self-esteem serves as a significant explanatory mechanism between both external and internal protective resources and psychological distress.
The present study has several limitations that should be considered when interpreting the findings. First, the cross-sectional and correlational design does not permit definitive conclusions regarding temporal precedence or causality, even though the proposed structural model was theoretically specified and showed acceptable fit. Second, participants were selected through convenience sampling from female heads of households in Shiraz, which may limit the generalizability of the results to women in other cities, rural areas, socioeconomic strata, cultural settings, or welfare circumstances. Third, all variables were assessed using self-report questionnaires, making the findings potentially susceptible to common-method variance, social desirability, recall bias, and differences in individual interpretation of questionnaire items. Fourth, several contextual factors that may influence anxiety and depression—including income, employment security, number and age of dependents, duration of household headship, marital history, physical health, stressful life events, receipt of formal welfare support, and quality of family relationships—were not incorporated into the structural model. Finally, although the model explained substantial proportions of the variance in self-esteem, depression, and anxiety, meaningful unexplained variance remained, indicating that additional psychological, familial, socioeconomic, and environmental factors contribute to mental health in this population.
Future studies should replicate the proposed model using longitudinal designs so that the temporal relationships among social support, resilience, self-esteem, anxiety, and depression can be examined more rigorously. Prospective studies with repeated measurements could determine whether changes in social support and resilience precede changes in self-esteem and whether these changes subsequently predict reductions in psychological distress. Probability-based and multicenter sampling across different provinces, urban and rural areas, and socioeconomic groups is recommended to improve generalizability and permit comparison across contextual conditions. Future research should also consider additional mediating or moderating variables, such as self-efficacy, loneliness, perceived stigma, emotion regulation, coping strategies, psychological capital, financial strain, family functioning, and social exclusion. Multi-group structural equation modeling could be used to determine whether model pathways differ according to age, employment status, income, number of children, duration of household headship, or receipt of formal support. Mixed-method studies may also provide a deeper understanding of how female heads of households experience support, resilience, and self-worth in everyday life. Finally, experimental or quasi-experimental research should investigate whether interventions specifically designed to enhance social support, resilience, and self-esteem produce corresponding reductions in anxiety and depression and whether changes in self-esteem statistically mediate intervention effects.
The findings have direct implications for psychologists, counselors, social workers, welfare organizations, and agencies serving female-headed households. Assessment programs should move beyond identifying anxiety and depression and routinely evaluate perceived social support, resilience, and self-esteem as potentially modifiable protective resources. Support organizations can establish structured peer-support groups, mentoring networks, family-support programs, and community-based services that reduce social isolation and provide both emotional and practical assistance. Psychological interventions should incorporate components aimed at strengthening self-esteem through identification of personal competencies, modification of negative self-beliefs, reinforcement of successful coping experiences, and development of a more stable sense of personal worth. Resilience-building programs can include stress-management skills, adaptive coping, problem solving, emotion regulation, goal setting, and preparation for recurring financial and family stressors. Because social support showed particularly strong associations with self-esteem and psychological distress, interventions should not focus exclusively on individual coping skills but should also strengthen the social environment surrounding female heads of households. Coordination among mental-health professionals, social welfare agencies, community organizations, and employment or financial-support services may therefore provide a more comprehensive approach to reducing psychological distress and improving long-term psychosocial functioning in this population.
Acknowledgments
The authors express their deep gratitude to all participants who contributed to this study.
Authors’ Contributions
All authors equally contributed to this study.
Declaration of Interest
The authors of this article declared no conflict of interest.
Ethical Considerations
The study protocol adhered to the principles outlined in the Helsinki Declaration, which provides guidelines for ethical research involving human participants.
Transparency of Data
In accordance with the principles of transparency and open research, we declare that all data and materials used in this study are available upon request.
Funding
This research was carried out independently with personal funding and without the financial support of any governmental or private institution or organization.
References
- 1. Harris O. Households as natural units. Of Marriage and the Market: Routledge; 2023. p. 136-56.
- 2. Torabi, Sadeghi HS, Ranjbari B. Female-headed households, vulnerability, empowerment, cluster analysis, Iran. Social Welfare and Development Planning. 2025;16(63):229-62.
- 3. Izadidastenaei Z. Mental health and related factors in Iranian female headed households. 14th International Nursing Research Congress2026.
- 4. Fathi, Shojaei Goodarzi A, Norouzi, Effat. Effectiveness of cognitive-behavioral therapy on divorce adjustment and psychological capital in female heads of households. Health Promotion Management. 2026;15(1):23-33.
- 5. Kumar A, Pramanik J, Goyal N, Chauhan D, Sivamaruthi BS, Prajapati BG, et al. Gut microbiota in anxiety and depression: Unveiling the relationships and management options. Pharmaceuticals. 2023;16(4):565. doi: 10.3390/ph16040565.
- 6. Rashid S, Qureshi AG, Noor TA, Yaseen K, Sheikh MAA, Malik M, et al. Anxiety and depression in heart failure: An updated review. Current Problems in Cardiology. 2023;48(11):101987. doi: 10.1016/j.cpcardiol.2023.101987.
- 7. Yaghoubi S, Rezaei, Zabardast, Azra. Prevalence of anxiety and depression among adolescent girls in Lahijan and associated demographic factors. Toloo-e-Behdasht. 2024;23(3):1-15.
- 8. Akbarpour, Fahimi, Rezaei. Relationship between physical activity level and symptoms of anxiety and depression in patients undergoing coronary angiography: The role of gender and age. Mind, Movement and Behavior. 2026;5(1).
- 9. Hashemi Z, Mohammadi-Fam M, Hekmati I, Shahjouei T. Relationship of perceived social support and ego strength with depression in older adults: The mediating role of cultural intelligence. Journal of Applied Psychology. 2026;20(1).
- 10. Kalateh S, Taherzadeh A. Relationship of social adjustment and social support with family health among workers: A case study of industrial towns in Ardakan. Industrial Sociology. 2025;1(1):23-40.
- 11. Ahrari E, Mesrabadi M, Seyedghasem. A meta-analysis of the relationship between social support and academic performance. Education and Evaluation. 2023;16(62):38-58.
- 12. Sufredini F, Catling C, Zugai J, Chang S. The effects of social support on depression and anxiety in the perinatal period: A mixed-methods systematic review. Journal of Affective Disorders. 2022;319:119-41. doi: 10.1016/j.jad.2022.09.005.
- 13. Yap MC, Wu F, Huang X, Tang L, Su K, Tong X, et al. Association between individual resilience and depression or anxiety among general adult population during COVID-19: A systematic review. Journal of Public Health. 2023;45(4):e639-e55. doi: 10.1093/pubmed/fdad144.
- 14. Cao X, Liu X. Self-esteem as a predictor of anxiety and academic self-efficacy among Chinese university students: A cross-lagged analysis. Current Psychology. 2024;43(22):19628-38. doi: 10.1007/s12144-024-05781-4.
- 15. Mandami H, Sayadi Touran H, Zarei Mahmoud M. A systematic review of supply-chain resilience studies after COVID-19. Production and Operations Management. 2023;14(2).
- 16. Greig HS, McHugh PA, Thompson RM, Warburton HJ, McIntosh AR. Habitat size influences community stability. Ecology. 2022;103(1):e03545. doi: 10.1002/ecy.3545.
- 17. Orth U, Robins RW. Is high self-esteem beneficial? Revisiting a classic question. American Psychologist. 2022;77(1):5. doi: 10.1037/amp0000922.
- 18. Farokhandeh-Fal M, Nejat P. The effect of social exclusion on state explicit and implicit self-esteem and the moderating role of trait self-esteem. Social Cognition. 2022;11(21):131-45.
- 19. Dalir, Heydari. The relationship between satisfaction and self-esteem in nursing students: A descriptive-correlational study. Navid No. 2025;28(95):7-19.
- 20. Cingel DP, Carter MC, Krause HV. Social media and self-esteem. Current Opinion in Psychology. 2022;45:101304. doi: 10.1016/j.copsyc.2022.101304.
- 21. Merino M, Tornero-Aguilera JF, Rubio-Zarapuz A, Villanueva-Tobaldo CV, Martín-Rodríguez A, Clemente-Suárez VJ. Body perceptions and psychological well-being: A review of the impact of social media and physical measurements on self-esteem and mental health with a focus on body image satisfaction and its relationship with cultural and gender factors. Healthcare. 2024;12(14):1396. doi: 10.3390/healthcare12141396.
- 22. Cao F, Li J, Xin W, Cai N. Impact of social support on the resilience of youth: Mediating effects of coping styles. Frontiers in Public Health. 2024;12:1331813. doi: 10.3389/fpubh.2024.1331813.
- 23. Farmakopoulou I, Lekka M, Gkintoni E. Clinical symptomatology of anxiety and family function in adolescents - the self-esteem mediator. Children. 2024;11(3):338. doi: 10.3390/children11030338.
- 24. Yıldırım M, Çağış ZG, Aziz IA, Rizzo A, Turan ME, Nucera G, et al. The mediating role of self-esteem in the relationship between social support and affective experiences among undergraduate students in Turkey. Acta Psychologica. 2024;250:104540. doi: 10.1016/j.actpsy.2024.104540.
- 25. Chu X, Chen Z. The associations between parenting and bullying among children and adolescents: A systematic review and meta-analysis. Journal of Youth and Adolescence. 2025;54(4):928-54. doi: 10.1007/s10964-024-02108-1.
Downloads
References
1. Harris O. Households as natural units. Of Marriage and the Market: Routledge; 2023. p. 136-56.
2. Torabi, Sadeghi HS, Ranjbari B. Female-headed households, vulnerability, empowerment, cluster analysis, Iran. Social Welfare and Development Planning. 2025;16(63):229-62.
3. Izadidastenaei Z. Mental health and related factors in Iranian female headed households. 14th International Nursing Research Congress2026.
4. Fathi, Shojaei Goodarzi A, Norouzi, Effat. Effectiveness of cognitive-behavioral therapy on divorce adjustment and psychological capital in female heads of households. Health Promotion Management. 2026;15(1):23-33.
5. Kumar A, Pramanik J, Goyal N, Chauhan D, Sivamaruthi BS, Prajapati BG, et al. Gut microbiota in anxiety and depression: Unveiling the relationships and management options. Pharmaceuticals. 2023;16(4):565. doi: 10.3390/ph16040565.
6. Rashid S, Qureshi AG, Noor TA, Yaseen K, Sheikh MAA, Malik M, et al. Anxiety and depression in heart failure: An updated review. Current Problems in Cardiology. 2023;48(11):101987. doi: 10.1016/j.cpcardiol.2023.101987.
7. Yaghoubi S, Rezaei, Zabardast, Azra. Prevalence of anxiety and depression among adolescent girls in Lahijan and associated demographic factors. Toloo-e-Behdasht. 2024;23(3):1-15.
8. Akbarpour, Fahimi, Rezaei. Relationship between physical activity level and symptoms of anxiety and depression in patients undergoing coronary angiography: The role of gender and age. Mind, Movement and Behavior. 2026;5(1).
9. Hashemi Z, Mohammadi-Fam M, Hekmati I, Shahjouei T. Relationship of perceived social support and ego strength with depression in older adults: The mediating role of cultural intelligence. Journal of Applied Psychology. 2026;20(1).
10. Kalateh S, Taherzadeh A. Relationship of social adjustment and social support with family health among workers: A case study of industrial towns in Ardakan. Industrial Sociology. 2025;1(1):23-40.
11. Ahrari E, Mesrabadi M, Seyedghasem. A meta-analysis of the relationship between social support and academic performance. Education and Evaluation. 2023;16(62):38-58.
12. Sufredini F, Catling C, Zugai J, Chang S. The effects of social support on depression and anxiety in the perinatal period: A mixed-methods systematic review. Journal of Affective Disorders. 2022;319:119-41. doi: 10.1016/j.jad.2022.09.005.
13. Yap MC, Wu F, Huang X, Tang L, Su K, Tong X, et al. Association between individual resilience and depression or anxiety among general adult population during COVID-19: A systematic review. Journal of Public Health. 2023;45(4):e639-e55. doi: 10.1093/pubmed/fdad144.
14. Cao X, Liu X. Self-esteem as a predictor of anxiety and academic self-efficacy among Chinese university students: A cross-lagged analysis. Current Psychology. 2024;43(22):19628-38. doi: 10.1007/s12144-024-05781-4.
15. Mandami H, Sayadi Touran H, Zarei Mahmoud M. A systematic review of supply-chain resilience studies after COVID-19. Production and Operations Management. 2023;14(2).
16. Greig HS, McHugh PA, Thompson RM, Warburton HJ, McIntosh AR. Habitat size influences community stability. Ecology. 2022;103(1):e03545. doi: 10.1002/ecy.3545.
17. Orth U, Robins RW. Is high self-esteem beneficial? Revisiting a classic question. American Psychologist. 2022;77(1):5. doi: 10.1037/amp0000922.
18. Farokhandeh-Fal M, Nejat P. The effect of social exclusion on state explicit and implicit self-esteem and the moderating role of trait self-esteem. Social Cognition. 2022;11(21):131-45.
19. Dalir, Heydari. The relationship between satisfaction and self-esteem in nursing students: A descriptive-correlational study. Navid No. 2025;28(95):7-19.
20. Cingel DP, Carter MC, Krause HV. Social media and self-esteem. Current Opinion in Psychology. 2022;45:101304. doi: 10.1016/j.copsyc.2022.101304.
21. Merino M, Tornero-Aguilera JF, Rubio-Zarapuz A, Villanueva-Tobaldo CV, Martín-Rodríguez A, Clemente-Suárez VJ. Body perceptions and psychological well-being: A review of the impact of social media and physical measurements on self-esteem and mental health with a focus on body image satisfaction and its relationship with cultural and gender factors. Healthcare. 2024;12(14):1396. doi: 10.3390/healthcare12141396.
22. Cao F, Li J, Xin W, Cai N. Impact of social support on the resilience of youth: Mediating effects of coping styles. Frontiers in Public Health. 2024;12:1331813. doi: 10.3389/fpubh.2024.1331813.
23. Farmakopoulou I, Lekka M, Gkintoni E. Clinical symptomatology of anxiety and family function in adolescents - the self-esteem mediator. Children. 2024;11(3):338. doi: 10.3390/children11030338.
24. Yıldırım M, Çağış ZG, Aziz IA, Rizzo A, Turan ME, Nucera G, et al. The mediating role of self-esteem in the relationship between social support and affective experiences among undergraduate students in Turkey. Acta Psychologica. 2024;250:104540. doi: 10.1016/j.actpsy.2024.104540.
25. Chu X, Chen Z. The associations between parenting and bullying among children and adolescents: A systematic review and meta-analysis. Journal of Youth and Adolescence. 2025;54(4):928-54. doi: 10.1007/s10964-024-02108-1.
Publication Timeline
- Submitted
- Revised
- Accepted
Issue
Section
License
Copyright (c) 2026 Shaghayegh Soleimani (Author); Reza Mirzaei

This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License.
